"RaftLabs has been an exceptional partner. From the start, they became more than just a service provider, they embraced our vision with their expertise and dedication. We're proud of the result."

Jennyfer Ngueno
CoFounder & CEO, Sekou
Healthcare Software Development Services
We build healthcare software for practices, clinics, and health systems: patient portals, telehealth, RPM, clinical decision support, and EHR integrations. HIPAA safeguards built in from week one. Fixed price, with a validated v1 first and the full platform grown from there.
HIPAA safeguards built in from the start, not bolted on before launch
Connects to your existing EHR, billing, scheduling, and wearable device feeds
Patient portals, telehealth, RPM, and clinical decision support built to your exact workflow
25+ clinics adopted our RPM platform in 60 days
Launch a validated v1 first, then grow it into the full platform
Bring the problem, the current workflow, or the existing code. We reply with a practical next step within one business day.
Trusted by
























The brief
Good software decisions begin with the constraint, not a list of features or a preferred technology.
Clinical staff spending 2+ hours a day on documentation instead of patient care?
EHR that doesn't talk to your billing system, scheduling tool, or patient portal?
Per-seat licensing fees that scale with your team, not your revenue?
Previous software that nobody fully understands anymore?
Plain answer
RaftLabs is a healthcare software development company. We build software for practices, clinics, and health systems: patient portals, telehealth platforms, remote patient monitoring, and integrations with the EHR you run, including Epic, Cerner, and Athenahealth. Engagements start with clinical workflow mapping and a fixed price agreed in writing, and we sign a Business Associate Agreement before patient data is handled.
What to remember
A nurse finishes a visit and spends the next twenty minutes re-keying the same numbers into systems that do not talk to each other. The EHR does not pass to billing. Billing does not pass to the patient portal. So someone types it all again, and the clinical staff you hired to care for patients spend two hours a day on documentation instead.
None of it is bad software. It is average software, sold to every practice the same way, and your workflow is not average. The per-seat license grows with your team, not your revenue, and the one person who fully understood the setup is no longer around.
Custom healthcare software removes the re-keying. The systems connect, the record is one record, and the workflow fits the way your clinic actually runs.
Generic clinical tools are built for the average practice. When your workflows, compliance requirements, or patient data do not fit the template, staff spend the day working around the software instead of using it.
RaftLabs has shipped healthcare products with HIPAA safeguards since 2015, for clients across the US, UK, Europe, Canada, and the UAE. A nurse-assisted telehealth platform onboarded 50+ clinics in its first 12 weeks. A remote patient monitoring platform reached 25+ clinics within 60 days, and we later added an AI layer to it. One team scopes the clinical workflow, builds the system, integrates it with your existing EHR, and hands it over, with HIPAA safeguards designed in from week one, not retrofitted before launch. That scope ranges from connecting to an existing record system, RaftLabs' EHR and EMR integration work, to building for patients directly through patient portal development.
Healthcare software failures do not fail quietly. According to the IBM Cost of a Data Breach Report 2025, the average healthcare data breach now costs $7.42 million, the highest of any industry for the 14th consecutive year. And a bad implementation does not need a breach to do damage: KLAS Research's 2024 survey of EHR go-lives found only 38% of implementations fully met the expectations set before the project started.
The two named incidents below are not hypotheticals. They are what happens when clinical software ships without the safeguards or the scoping discipline built in from day one.
MD Anderson's rollout is the textbook case: the system itself worked, but the rollout did not account for how the clinical and billing workflows actually ran, and the disruption drove the loss and the roughly 900 layoffs that followed. The Oracle Health breach makes the second point: when the vendor's systems are the ones breached, your patients' data is exposed anyway. Both failures trace back to the same root: safeguards and scoping treated as later phases instead of week-one work. That is why every engagement on this page starts with the workflow map and the compliance architecture, not the feature list.
Everything on the left should already be true for your practice. Even one thing on the right, and a configured off-the-shelf tool is the smarter spend right now.
A clinical workflow, compliance requirement, or patient-data structure that off-the-shelf healthcare tools can't fit.
An existing EHR, billing, or scheduling system the new software has to connect to, not replace.
A decision-maker who can sign off on scope, and budget for a fixed-price build.
A standard need a configured practice-management or EHR product already covers well.
No budget yet and requirements still forming.
Shopping for the cheapest hourly team, not a fixed-scope partner.
It is whether custom healthcare software is the right answer at all. We use four possible recommendations before discussing a development scope.
Choose a maintained product when it handles the core workflow and the remaining gaps can be solved with configuration, a connector, or a small process change. Paying for healthcare software you do not have to maintain is often the better trade.
Keep the existing product when users still get value from it and the code can be understood safely. Start with evidence: where the code lives, how the data is organized, what is tested, which outside services it depends on, who can access what, and how updates go live.
Own healthcare software when the workflow shapes margin, customer experience, speed, or a product customers pay for. Start with one complete path and the system connections that path cannot work without.
Do not turn a changing policy into permanent software. Stabilise the rules, name the workflow owner, and measure the cost of the current process before paying for a product.
Not sure which path is yours? Bring it to a 30-minute call. Leave with the answer in writing.
Healthcare products must account for clinical workflows, compliance risks, data interoperability, and the business decision to buy, build, or wait. Explore the challenges healthcare teams face and how to evaluate the right approach.
What we build
HIPAA-compliant iOS and Android apps for patients and clinicians: telehealth, medication management, RPM companion apps, and health tracking, built in React Native or native Swift and Kotlin where performance demands it.
Multi-tenant healthcare SaaS with subscription billing, tenant isolation for PHI, and self-service onboarding, architected so cost-per-clinic and enterprise readiness are decided in sprint one.
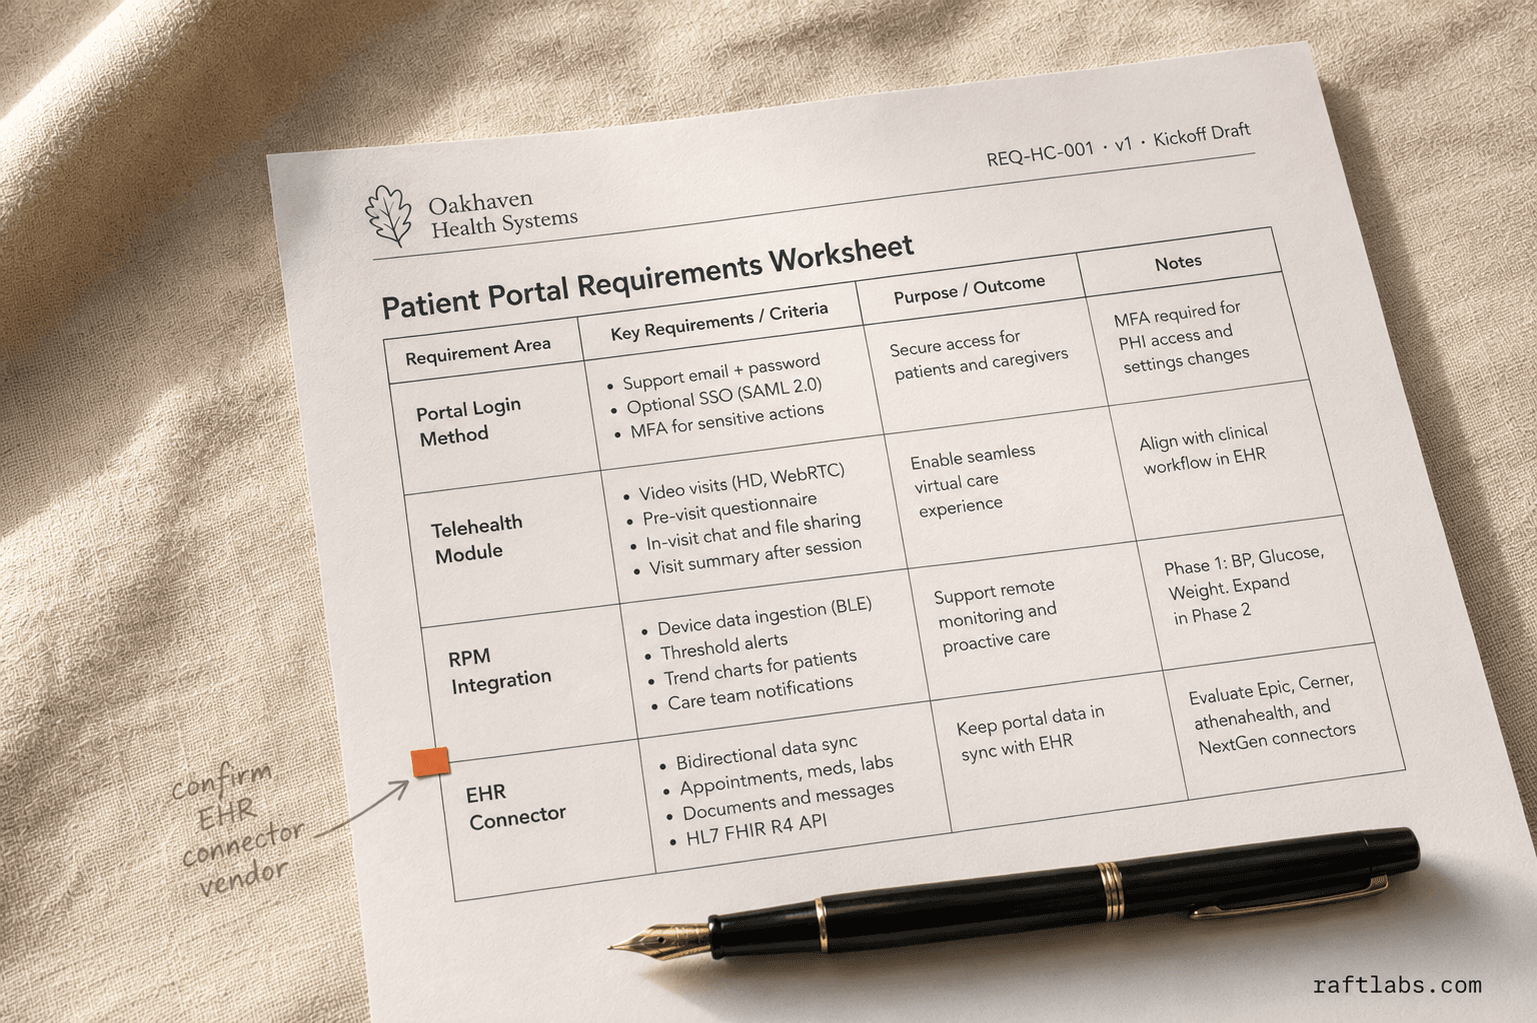
Bidirectional EHR connectivity via HL7 FHIR R4 and HL7 v2: Epic App Orchard, Cerner FHIR Millennium, Athenahealth, and Meditech, for demographics, appointments, clinical notes, results, and medication lists.
Secure patient portals for scheduling, records access, secure messaging, and results, wired to your EHR so patients and staff work from one record, not two parallel systems.
RPM platforms that ingest data from CGM, blood pressure monitors, pulse oximeters, and connected scales, with automated threshold alerting and a provider dashboard for chronic care programs.
HIPAA-eligible video sessions, secure messaging, and asynchronous consultation workflows on Twilio Video or Daily.co WebRTC, with EHR integration for scheduling and clinical documentation.
Automation for prior authorization, patient intake, scheduling, and billing, cutting the manual documentation and data re-entry that pulls clinical staff away from patient care.
We have shipped a nurse-assisted telehealth platform that onboarded 50+ clinics in its first 12 weeks and a remote patient monitoring platform 25+ clinics adopted within 60 days. That domain knowledge shapes every architecture decision from week one, so you do not pay for us to learn what the HIPAA Security Rule's technical safeguards mean or what an Epic or Cerner integration needs to pass vendor review.
Milestone-based pricing with the fixed total agreed and documented before development starts, not a time-and-materials contract where the number depends on hours logged. The project breaks into milestones, each with a defined deliverable and payment, and you see working software at every bi-weekly sprint review. If scope changes, the change is costed and approved explicitly before any additional work begins.
No handoffs between a business analyst who scoped it, a design team who doesn't know the clinical workflow, and an offshore build team who has never spoken to the client. The same engineers who run discovery and review the wireframes with your clinical team are the ones who write the code, so accountability never gets diluted across a handoff chain.
Every dependency is chosen because it is fit for healthcare, not because it is the most popular option. Web interfaces and patient portals, cross-platform mobile, and PHI storage with row-level security, plus a health-specific layer for EHR connectivity, HIPAA-eligible video sessions, and device integrations for CGM, blood pressure, and pulse oximetry.
We connect the new system to your existing EHR, billing software, scheduling tool, and third-party device feeds. No rip-and-replace: your staff keeps the systems they know, and the new platform adds capabilities without creating two parallel records for every patient. Every integration is tested against a sandbox instance of your EHR before any production cutover.
Support after launch is arranged as another fixed phase or an ongoing engagement, or handed to your own team with the operating notes. Real patient load surfaces clinical workflow edge cases no test pass catches, most of them early; whoever runs the system investigates the monitoring alerts and handles bug fixes and performance tuning as those cases surface.
Healthcare software operates under multiple overlapping regulatory frameworks. We scope compliance requirements in week one and build them into the architecture before any code is written.
We build to the HIPAA Security Rule's administrative, physical, and technical safeguards: PHI encrypted at rest (AES-256) and in transit (TLS 1.3), multi-factor authentication, role-based access control, session timeout enforcement, and immutable audit logs recording every PHI access event. The HITECH Act's breach-notification duties shape the logging and monitoring design, so an incident is detectable and reportable inside the 60-day window. Business Associate Agreements cover AWS, Twilio, Stripe, and every provider that touches patient data.
When you sell into hospitals and payers, their vendor-security review asks for SOC 2. We build with the Trust Services Criteria in mind from sprint one: change management, access logging, encryption, and third-party vendor management documented as the system is built, not reconstructed the week before the audit. We are not your auditor, but we build so a SOC 2 Type II report is a reporting exercise rather than a re-architecture.
EHR integration via HL7 FHIR R4 APIs for patient demographics, appointments, clinical notes, results, and medication lists. Epic App Orchard, Cerner FHIR Millennium, and Athenahealth API connectivity. For systems without a FHIR-capable API, HL7 v2 message-based integration handles bidirectional data exchange.
For platforms required to support ONC Cures Act Final Rule compliance, we implement SMART on FHIR authorization, FHIR R4 patient access APIs, and the audit logging required for ONC compliance reviews. Information-blocking prohibitions are accounted for in the data access design.
For platforms serving European patients, we scope GDPR requirements: data processing agreements, consent management, right-to-erasure workflows for patient records, and data residency controls keeping PHI within EU infrastructure. UK GDPR requirements for post-Brexit deployments are handled separately where applicable.
For software as a medical device (SaMD), we scope regulatory classification, document software development lifecycle requirements for the target classification, and prepare quality management system documentation for regulatory submission.
DICOM-compliant image handling for platforms that store, transmit, or display medical images. PACS integration, DICOM viewer embedding via open-source renderers (OHIF, Cornerstone.js), and compliant storage on HIPAA-eligible infrastructure with appropriate encryption and access controls.
AI in healthcare software is not one thing. There is the back-office layer, prior-authorization drafting, documentation summarization, intake triage, where a wrong answer means a human catches it. And there is the clinical-decision layer, where a wrong answer reaches a patient. We build aggressively in the first and conservatively in the second. That is where the honest wins are: taking the two hours a day of re-keying off clinical staff, not replacing clinical judgment.
Where we hold the line: any AI output that informs a clinical decision ships with a clinician in the loop, a full audit trail, and drift monitoring. The moment a model drives diagnosis or treatment without a clinician's sign-off, it crosses into software-as-a-medical-device territory (FDA 21 CFR Part 11, IEC 62304), and that is a regulatory program, not a feature. We scope that line in week one, so you know which side of it your build sits on before you commit the budget.
In healthcare, the software has to work every time. We build systems that handle the load, stay compliant, and connect to what you already use.
Custom healthcare software designed around your specific clinical workflow, not configured from a vendor template built for a different care model: telehealth platforms, remote patient monitoring, HIPAA-compliant EHR/EMR tools, chronic disease management, medication adherence, and clinical decision support. Each build starts with a one-week discovery mapping the clinical workflow with your care team.
Custom clinical and operational analytics dashboards that surface the KPIs your leadership and clinical teams need, built from your actual data: operational views for practice managers, clinical quality views for medical directors, and population health views for value-based care contracts. All dashboards pull from your existing EHR, billing, and RPM data without manual export, refreshed daily or in near-real-time.
Replace legacy EHR systems, outdated patient portals, and desktop-only clinical software with modern, secure, maintainable platforms, without the clinical disruption of a hard cutover. We use a strangler fig pattern: the new system runs alongside the legacy one, workflows migrate one at a time, and data migration is validated with reconciliation checks before any cutover.
Connect your new or existing platform to the clinical systems already in use: EHR integration via FHIR R4, e-prescribing, plus scheduling, billing, and telehealth video infrastructure. Each integration is assessed for the correct API approach and tested against the vendor's sandbox before production, so data flows without manual re-entry.
Reduce page load times, cut database query latency, and automate the manual steps that slow clinical and administrative staff. We audit first, profiling the application against production traffic to find the specific queries and rendering paths causing slowdowns, then produce a fix list ranked by time saved per day for clinical staff. Results are verified with load testing under simulated clinical workload.
Intelligent healthcare software using AI where it delivers measurable improvement, not AI applied broadly because it is a trend. Examples: risk stratification models trained on your EHR data, AI-assisted symptom triage before telehealth visits, clinical decision support using RAG over your clinical knowledge base, and automated prior authorization assistance. Every model ships with an audit trail, human review for any output used in a clinical decision, and drift monitoring.
We are not tied to one framework. We pick the stack that fits your compliance, integration, and handover needs, then document every choice so any competent engineering team can maintain it. Every dependency is chosen because it is fit for healthcare, not because it is the most popular option in a non-clinical context.
| Layer | Technologies we use | Where it fits |
|---|---|---|
| Frontend | React, Next.js, TypeScript, React Native | Patient portals, clinician dashboards, and cross-platform mobile apps |
| Backend | Node.js, Python (FastAPI, Django), .NET | Clinical data processing, APIs, and business logic |
| Databases | PostgreSQL (row-level security), MongoDB | PHI storage with least-privilege access and flexible clinical schemas |
| Interoperability | HL7 FHIR R4, HL7 v2, EHR and EMR APIs | Epic, Cerner, Athenahealth, and Meditech data exchange |
| Cloud and compliance | AWS, Azure, HIPAA-eligible services | Encrypted, audited infrastructure covered by Business Associate Agreements |
The rule holds at every layer: PHI encrypted at rest and in transit, no proprietary frameworks that lock you in, and no stack we cannot hand to your team on day one. The interoperability layer does the heaviest lifting, and we scope it early through our EHR and EMR integration work so clinical data flows without manual re-entry.
Walk us through your clinical workflow and what your current systems can't handle. We'll scope the build and give you a fixed cost.
How it works
Every project follows the same four phases. Scope is locked and price is fixed before development starts.
We map your clinical workflows with the care team who will use the software daily. You leave week 1 with a written scope document, integration assessment, and a fixed-price quote. No development starts without your sign-off.
HIPAA controls, EHR integration approach, and PHI data flows are designed before any code is written. Wireframes reviewed and approved by your clinical leads. The compliance architecture is documented and locked before the build starts.
Working software at a staging URL by the end of sprint one. Bi-weekly demos with the clinical team who will use it. QA and HIPAA compliance checks run in parallel with every sprint, not as a phase at the end.
Production deployment with monitoring activated on launch day. Support after launch is arranged as another fixed phase or an ongoing engagement, or handed to your own team: monitoring alerts investigated, bug fixes, and performance tuning as real patient load surfaces edge cases.
Overlaps are intentional — phases start before the previous one ends.
Proof
We've built HIPAA-compliant healthcare software for US practices and health systems. Here's what makes the difference.
A first shippable slice, one core module or workflow, goes live first. Week 1 produces a scoped, validated architecture: clinical workflow mapping, integration assessment, and wireframes reviewed with your care team. Bi-weekly sprints add scope from there, with working software at each review, UAT, and a HIPAA compliance review before deployment. Full platforms with AI and deep EHR integration grow from there.
HIPAA compliance is designed into the architecture from the first technical decision, not added as a checklist item at the end of the build. Every system ships with PHI encrypted at rest and in transit, multi-factor authentication, role-based access control with least privilege, immutable audit logs of every PHI access event, and Business Associate Agreements with every infrastructure provider that handles PHI. A compliance review before production deployment verifies all controls are implemented as designed.
We map your clinical workflows in Week 1 through structured sessions with the people who will use the software daily: nurses, physicians, front desk, and billing coordinators. The workflow they describe is always different from what the practice manager assumes, and that map drives the technical design before the database schema is finalized, not retrofitted after. Week 1 ends with a signed-off scope document and wireframes your clinical leads have approved.
Scope and cost locked before development starts in a written fixed-price proposal that defines the feature set, integration scope, compliance controls, and delivery timeline. The price you approve in Week 1 is the price you pay at the end. Changes to scope are addressed via a change request process: the change is specified, sized, costed, and approved before any additional work begins, so our incentives stay aligned with yours.
You see working software every two weeks in a live sprint demo with your clinical leads present: not slides, not screenshots, the actual running system demonstrated against real clinical scenarios by the engineer who built the feature. Problems that affect the clinical workflow surface early, when the fix is a day's work, not at the UAT review in Week 13. Issues raised at each demo are logged, prioritized, and resolved in the next sprint.
Direct access to your named project team throughout the engagement, the lead engineer, the project manager, and the QA lead, not a ticketing system or an account manager relaying messages. Weekly sync calls follow a structured agenda, with a written summary sent within 2 hours so decisions are documented. When a risk surfaces, an unavailable EHR sandbox or a slow compliance review, you hear about it the same day we know.
We provide fixed-price proposals after a scoping session. Scope, integration count, and compliance requirements are the primary cost drivers.
| Software type | What the first release covers |
|---|---|
| Patient portal | Scheduling, records access, secure messaging wired to the EHR |
| Telehealth platform | Video sessions, scheduling, clinical documentation |
| Remote patient monitoring | Device integration, threshold alerts, provider dashboard |
| EHR integration | FHIR R4 or HL7 v2 connectivity for the target system |
| Clinical data analytics and reporting dashboard | Operational and clinical dashboards from existing EHR, billing, and RPM data |
| Healthcare mobile app | iOS, Android, or cross-platform patient or clinician app |
| Complex platform | AI, RPM, EHR, and telehealth combined in one program |
Typical fixed prices, by project type: a patient portal runs $40K to $90K over 12 to 20 weeks, a telehealth platform $60K to $140K over 16 to 28 weeks, and an AI-enabled RPM system $100K to $250K over 24 to 40 weeks. EHR integration complexity is the largest cost variable.
Every engagement is fixed-price: scope, features, integrations, and compliance controls agreed and documented in writing before development starts. Cost changes only when scope changes, and scope changes are priced and approved explicitly before additional work begins.
Where you land depends on scope, not negotiation:
What it costs
A defined scope, integration list, and compliance controls, agreed and documented in writing before development starts.
HIPAA compliance review and QA testing are part of the build, not billed separately later. Cost changes only when scope changes, priced and approved before any additional work begins.
Starting investment
Starts at $10K
Scope and timeline agreed before development starts. Most teams start with one core module and expand once compliance controls are proven. After a 30-minute call, you get a written build, buy, repair, or wait recommendation plus first-phase direction. Free, whether or not you build with us.
No hourly billing
Scope and cost for each phase are locked in a written proposal before development starts. No hourly billing, no surprise invoices. A scope change is specified, sized, costed, and approved before any additional work begins.
HIPAA compliance
HIPAA compliance is designed into the architecture from the first technical decision: PHI encrypted at rest and in transit, role-based access control, immutable audit logs, and Business Associate Agreements with every infrastructure provider that handles patient data.
Proof
Three-year average engagement. Founders and operators describing the work in their own words. No marketing varnish.
"RaftLabs has been an exceptional partner. From the start, they became more than just a service provider, they embraced our vision with their expertise and dedication. We're proud of the result."
Jennyfer Ngueno
CoFounder & CEO, Sekou
Work with us
Bring the rough workflow, half-built product, or messy brief. We will map the smallest useful first move, then send scope, timeline, and price in plain English.
Straight answers to what buyers ask before they scope. Still stuck? .
Every engagement starts with discovery in week one: stakeholder interviews and clinical workflow mapping with the team who will use the software daily. You then get a written scope and a fixed price before any code is written. The build runs in two-week sprints with a live demo at every review, QA and a HIPAA safeguards review run alongside development. Most teams start with a validated v1, one core module or workflow, and grow the full platform from there.
First phases start at $10K, at a fixed price agreed and documented before development starts. Typical ranges: a patient portal runs $40K to $90K, a telehealth platform $60K to $140K, and an AI-enabled remote patient monitoring system $100K to $250K. The price includes the HIPAA safeguards review and QA testing. EHR integration complexity is the largest cost variable. The price changes only when scope changes, and a scope change is priced and approved before any extra work begins.
A patient portal typically takes 12 to 20 weeks, a telehealth platform 16 to 28 weeks, and an AI-enabled RPM system 24 to 40 weeks. We launch a validated v1 first, a core portal or a single EHR integration, then grow it. The first number we give you is the first shippable slice, not the whole product, and you see working software at every two-week sprint review instead of at the end of a long silence. The calendar holds more than coding: HIPAA controls are designed and reviewed, the EHR integration is tested against a sandbox of your actual system, and a security review runs before launch. Those steps sit inside the ranges above, not on top of them.
Yes. We sign a Business Associate Agreement on every project that handles protected health information, before we access any patient data, and every infrastructure provider we use (AWS, Twilio, Stripe) is covered by a BAA before the first byte of patient data is processed. The obligation itself is yours: HIPAA reaches any system that holds patient information, including a simple appointment-request form, and its penalties include a tier for violations you did not know about. Compliance is shared. We design the technical controls into the architecture from the first decision: encrypted storage, role-based access control, and audit trails on every access to patient data. Your practice still owns its policies, staff training, and the evidence an auditor asks for, and scoping names which controls the build covers and what your team still produces. No software purchase makes a practice compliant on its own.
Yes. We build two-way EHR connectivity over HL7 FHIR R4 and HL7 v2, including Epic App Orchard, Cerner FHIR Millennium, Athenahealth, and Meditech, covering demographics, appointments, clinical notes, results, and medication lists. The integration is scoped against your actual EHR instance in week one, before the fixed price is written, because whether your system exposes FHIR R4 or only HL7 v2 is the most common reason healthcare integration budgets blow up. Every integration is tested against a sandbox instance before any production cutover.
You do, fully, from day one. The code, the architecture, and the patient data are yours, and the cloud and hosting accounts the system runs on are in your name, so you hold practical control as well as legal ownership. There is no lock-in clause and no proprietary framework your next team cannot maintain. Every architectural decision is documented so any competent engineering team can pick up the work.
We built a nurse-assisted telehealth platform (video consultations, connected exam camera, otoscope, and stethoscope feeds, e-signed prescriptions) that onboarded 50+ clinics in its first 12 weeks, and a remote patient monitoring platform connected to CGM and blood pressure devices that 25+ clinics adopted within 60 days. We later added an AI layer to that RPM platform that cut clinical decision-making time by 20%. We work to the HIPAA Security Rule and HITECH breach-notification duties, and to HL7 and FHIR for data exchange. When a platform will sell into hospitals or payers, we build it ready for their SOC 2 vendor review. That is readiness built into your system, not a certification RaftLabs holds.
For mobile: React Native for cross-platform apps, Swift for iOS, Kotlin for Android. Backend: Node.js, Python, PostgreSQL, and AWS. For compliance: encrypted storage, audit logging, and role-based access control. For integrations: HL7 FHIR APIs for EHR connectivity, Twilio for telehealth, Stripe for billing. The stack fits your specific requirements, not our defaults, and every choice is documented so your team can maintain it.
Security is the day-to-day practice, separate from the HIPAA obligations above. Penetration testing is taken care of as part of the build. Our team never works with production patient data in development; we build and test with sample data instead. Backups are tested, not just scheduled, and set offboarding steps remove a person's access when they leave the team. Access inside the system follows least privilege, with role-based controls and an audit trail on every access to patient data. The third-party services the system depends on, such as hosting, video, and payments, are named in your scope document, including any that process patient data.
Support after launch is arranged as another fixed phase or an ongoing engagement, or your own team can run the system; the documentation is written so either works. Real patient load surfaces edge cases no test pass catches, so whoever runs the system watches the monitoring alerts and handles bug fixes and performance tuning as those cases come up. Whoever maintains it, a live system carries standing costs: hosting, EHR and API access fees, and security updates. Those costs exist from launch day, and scoping names them before you sign, not after.
You already hold everything. The code, the architecture notes, and the patient data are yours from day one, and the cloud and hosting accounts run in your name, so there is nothing you need to extract from us to leave. Every architectural decision is documented as we go, so another team can pick the system up and run it. We do not use source-code escrow, because you never depend on us releasing what is already yours.
You talk directly to the team doing the work, and the work runs on five principles. Switch to async: updates and decisions do not wait for a meeting. Be prepared: questions and the state of the work are written down before any call. Write: decisions and progress sit in writing where both sides can see them, in plain language. Ask and tell: problems are raised early, including bad news, not saved for a deadline. Own: one named person is answerable for each piece of work. You also see working software at every two-week review, not a status report about it.
Yes. We sign your NDA before anything sensitive is shared, and scoping information stays confidential. The NDA is the first protection, not the only one: the contract also assigns the code, the architecture, and the data to you, which is what protects the work itself once it exists.
No. The team that scopes your clinical workflow is the team that builds the system. The engineers who run discovery and review the wireframes with your clinical leads are the ones who write the code, and you can talk to them directly throughout. Our teams work from India & Ireland, and the people on your calls are the people on your project.