Telehealth platform for remote care
- 14 weeks
- initial product build
- 50+ clinics
- onboarded within 12 weeks
Healthcare SaaS Development
RaftLabs builds healthcare SaaS for funded digital health teams and clinical software vendors that need to turn a validated workflow into a multi-tenant product. We map where PHI enters, which parties and vendors handle it, how each role is authorized, what the EHR can actually expose, and which evidence a clinic buyer will request. Start with the smallest production release that proves the workflow and operating model, then add tenants, integrations, and modules from a stable foundation.
PHI data-flow and regulated-party mapping before architecture is approved
Tenant isolation, role-specific access, audit controls, and recovery designed from the buyer's real workflow
EHR feasibility checked against vendor documentation, customer authorization, and required read or write scopes
Acceptance evidence, operating runbooks, source code, and deployment configuration included in the agreed scope
Bring the problem, the current workflow, or the existing code. We reply with a practical next step within one business day.
The brief
Good software decisions begin with the constraint, not a list of features or a preferred technology.
Do pilot clinics keep asking compliance and integration questions your current architecture cannot answer?
Does your single-tenant product need to become a repeatable SaaS without exposing one customer's records to another?
Plain answer
RaftLabs provides healthcare SaaS development for digital health teams. A healthcare MVP with HIPAA scope typically costs $40,000-$90,000 and takes 16-26 weeks; a broader platform grows to $90,000-$160,000. One telehealth product was built in 14 weeks and onboarded 50+ clinics.
What to remember
Healthcare SaaS development turns a clinical or care-operations workflow into a product that multiple organizations can buy and operate. The hard part is the system around the screens: every PHI path needs an owner, every role needs a defensible access boundary, every tenant needs an isolation and recovery model, and every EHR promise needs a verified technical contract.
For a CTO or product leader preparing for clinic pilots, the first goal is to make one valuable workflow deployable, supportable, and reviewable by a healthcare buyer. That focused release creates evidence for the next integration or module without hiding foundational work.
The project should begin with a named user, a defined data path, and a pilot outcome. If those are still assumptions, validate them before funding a production platform.
A clinic, health system, or clinical software buyer has validated one workflow and needs a product it can pilot.
The product creates, receives, maintains, or transmits PHI and needs documented controls and vendor boundaries.
An existing single-tenant product has demand from more customers and needs a controlled multi-tenant migration.
The pilot depends on a specific EHR, device, video, messaging, or billing path that can be checked before the quote.
The target user and problem are still broad, so a workflow prototype or customer research is the next useful step.
An existing configurable product already covers the workflow and differentiation would come only from branding.
The plan assumes every EHR exposes the same data and write operations without customer-specific verification.
A serious discovery phase resolves six questions before it locks the schema or cloud design. These decisions become the architecture brief and the acceptance plan.
The output should be reviewable by engineering, product, security, privacy, and the pilot customer. If a proposal jumps from feature list to development without these decisions, its timeline is carrying unknown regulatory and integration work.
HHS says the HIPAA Security Rule requires reasonable and appropriate administrative, physical, and technical safeguards for ePHI. It also describes the rule as flexible, scalable, and technology neutral. That means HIPAA does not prescribe one database pattern or a marketing-friendly pair of encryption versions for every system. The regulated entity evaluates its risks, selects reasonable measures, documents decisions, reviews activity, and updates safeguards as the system changes.
The build translates that obligation into product and operating controls:
identity, authorization, and negative tests for each user and service role;
mechanisms to record and examine activity in systems that contain or use ePHI;
integrity, transmission, backup, restore, emergency-mode, and incident procedures appropriate to the system;
data minimization and retention decisions across production and secondary tools;
a dependency register that identifies which party operates each control;
evidence that the controls were tested before a pilot handles real data.
The HHS minimum-necessary guidance is a strong design input for permissions, even though the rule has defined exceptions and must be applied to the actual use or disclosure. We convert the approved policy into role, object, field, export, and support-access rules rather than treating a job title as sufficient authorization.
HHS also explains that a covered entity needs appropriate written assurances before a business associate handles PHI, and a business associate has corresponding obligations for a subcontractor that handles PHI on its behalf. Its business associate guidance includes definitions and exceptions, so we build a data-flow and vendor inventory for the responsible legal or privacy owner to decide which agreements are required.
RaftLabs does not sell an HHS certification. HHS states that it does not certify people or products as HIPAA compliant. We implement and document the technical scope your organization approves, while your organization and advisers own the legal determination, policies, workforce procedures, vendor agreements, and ongoing operation.
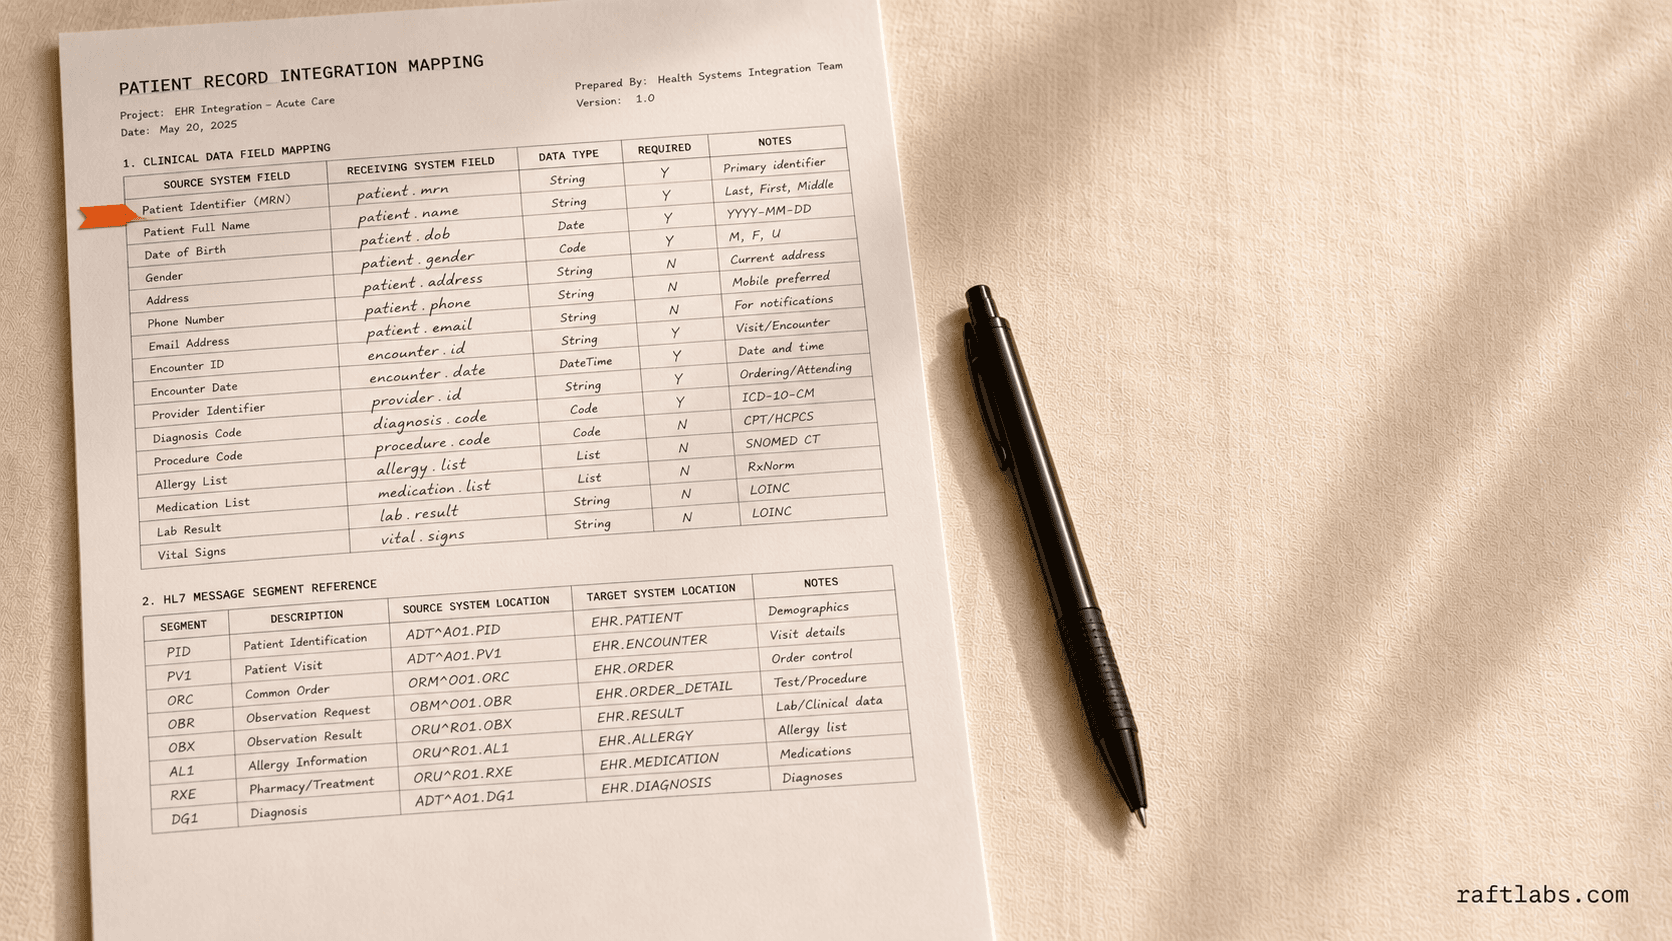
FHIR R4 defines resources and an API framework for exchanging healthcare information. It does not guarantee that every EHR customer exposes every resource, grants every scope, permits every write, or uses the same onboarding process.
Epic, Oracle Health, and athenahealth each publish developer material. Epic on FHIR lists APIs, specifications, testing, and client registration. Oracle Health Millennium Platform documentation covers FHIR R4, sandboxes, application registration, authorization, and tenant-specific access. athenahealth's developer portal documents its available APIs. Those sources establish possible capabilities. The target customer's configuration and authorization establish the project scope.
Before estimating an EHR integration, we verify:
The acceptance test follows the clinical workflow, not a list of endpoints. For example, “a coordinator can identify an eligible patient, schedule the approved service, and see the confirmed result in the system of record” is testable. “FHIR integration included” is not.
Multi-tenancy is a set of isolation and operating decisions. We compare at least three patterns before choosing one.
| Pattern | Where it can fit | What must be proved |
|---|---|---|
| Shared schema with tenant identifiers | Products that need efficient aggregate operations and can enforce one policy consistently | Every query, background job, cache, export, file, and administrative path applies the tenant boundary; negative tests attempt cross-tenant access |
| Schema per tenant | Products that benefit from a clearer logical boundary and can manage more schema operations | Provisioning, migrations, connection handling, reporting, backup, and restore work consistently across all tenant schemas |
| Database or account per tenant | Buyers that require stronger isolation, separate keys, customer-specific location, or independent restore | Automated provisioning, deployment, migrations, monitoring, cost allocation, and aggregate reporting remain operable as tenant count grows |
The choice is documented with its rejected alternatives. A team should be able to explain how it restores one clinic, rotates a tenant-specific secret, runs an aggregate report, applies a schema change, and proves that a support user cannot browse another clinic's records.
Core scope
The examples below are limited to results stated in current RaftLabs portfolio pages. They show delivery of telehealth and remote monitoring products; they do not prove a separate compliance certification or every capability described on this service page.
Proof
The telehealth case study documents a 14-week build with provider and patient portals, video visits, scheduling, secure messaging, and EHR integration. It reports that more than 50 clinics were onboarded within 12 weeks and in-person visits fell by 60%.
The remote patient monitoring case study documents a 14-week build connecting more than four wearable types to patient and provider workflows.
| Buyer question | Evidence a credible proposal should contain |
|---|---|
| What is the first sellable workflow? | Named buyer, users, start and end state, excluded modules, and measurable acceptance cases |
| Where does PHI travel? | Field-level data-flow map covering vendors, logs, analytics, support, backups, and exports |
| Who is responsible for each HIPAA decision? | Regulated-party assumptions, client legal and privacy owners, vendor register, and control ownership |
| How is tenant isolation enforced? | Chosen pattern, policy location, negative tests, provisioning, migration, export, deletion, and restore plan |
| Is the EHR integration actually available? | Target customer, endpoint, FHIR version, resources, operations, scopes, sandbox, registration, approval, and failure handling |
| What happens when an integration fails? | Retry, reconciliation, alert, manual recovery, and support ownership for each critical operation |
| What does the buyer receive? | Code and account ownership, architecture decisions, tests, deployment configuration, evidence, runbooks, and exclusions |
| What determines the next phase? | Pilot measures tied to workflow completion, reliability, support load, and buyer feedback |
A proposal that promises “HIPAA compliant,” “FHIR integrated,” and “multi-tenant” without these artifacts is naming outcomes without defining how they will be accepted.
RaftLabs uses its published pricing model across service pages. For a healthcare platform with HIPAA scope, the canonical planning range is $40,000-$90,000 for an MVP and $90,000-$160,000 for a fuller product. The typical 16-26 week window depends on the workflow, tenant model, integrations, mobile clients, migration, and evidence required for launch.
The first quote follows the smallest production release that can satisfy the pilot. We do not remove required security, recovery, or integration work to manufacture a lower entry price. When an external dependency remains uncertain, a proof phase resolves it before the production commitment.
What it costs
Start with one production workflow and the complete tenant, data, integration, evidence, and handover path it needs.
Your first release should prove that one clinic can operate the workflow and that the team can support it. Additional EHRs, mobile clients, white-labelling, and modules earn their place from pilot evidence.
Starting investment
Starts around $40,000
Healthcare SaaS MVPs commonly fall between $40,000 and $90,000 and take 16-26 weeks. A broader platform grows to $90,000-$160,000 in defined releases.
Assumptions are visible before the quote
The scope names the customer, workflow, PHI paths, external dependencies, tenant model, client decisions, acceptance evidence, and exclusions used to create the range.
Handover is part of the release
The contract identifies the code, configuration, tests, diagrams, evidence, runbooks, accounts, licenses, and dependency terms the client will receive or continue to operate.
Useful next steps
Work with us
EHR Integration Services
See the serviceTry it yourself
HIPAA Compliance Checklist
30+ requirements, plain-English, filtered to what you're building.
Open the free tool
Article
Medspa Management Software: Build vs. Buy for Multi-Location Chains (2026)
Aesthetic Record costs up to $699/month per location. A 15-location chain pays over $125,000 a year for software that still cannot sync loyalty points across sites or generate a single roll-up P&L. Here is when custom medspa management software makes financial sense, what it costs, and what the first 90 days look like.
Read more
Article
Cost to Build an App Like Headspace or Calm: What a Meditation App Really Takes
A cost-first guide for wellness brands, creators, and corporate teams scoping a meditation app. Real build ranges ($40K-$220K+), the subscription economics behind Calm and Headspace, V1/V2/V3 phasing, and when to build custom instead of white-labeling.
Read more
Article
Healthcare CRM software: Build vs. buy in 2026
Salesforce Health Cloud costs $300-500/user/month. Epic's CRM requires a $1M+ implementation. Custom healthcare CRM starts at $120K. Here's how to decide which actually fits your operation.
Read more
Article
Cost to Build a Quick Commerce App Like Blinkit: Features and What Actually Ships
Real quick commerce app development costs, phased feature breakdown, and why Shopify delivery plugins and WooCommerce dark store plugins fail at scale. Built for grocery chains, pharmacy networks, and dark store operators.
Read moreNo development company can give you an HHS product certification. HHS says it does not certify people or products as HIPAA compliant, and private certifications do not remove a regulated entity's legal obligations. A development partner can map PHI, implement agreed safeguards, produce technical evidence, and work with your legal, privacy, security, and clinical owners. Your organization remains responsible for determining its obligations and operating the controls after launch.
Choose one buyer, one clinical or operational workflow, and one measurable acceptance outcome. A credible first release usually includes tenant provisioning, the roles needed for that workflow, minimum-necessary access decisions, the required PHI paths, activity records, recovery procedures, and one proven integration path if the workflow depends on external data. Reporting, white-labelling, native apps, and additional EHRs should enter the first phase only when the pilot cannot operate without them.
The RaftLabs planning range for a healthcare platform with HIPAA scope is $40,000-$90,000 for an MVP and $90,000-$160,000 for a fuller build, usually across 16-26 weeks. A non-production architecture or integration proof may fit the $8,000-$20,000 and 3-6 week proof-of-concept band. The quote depends on workflow count, tenancy, EHR access, mobile clients, migration, evidence, and launch obligations.
The correct test is whether the party is acting as a business associate or subcontractor and creates, receives, maintains, or transmits PHI in that role. HHS documents both the business associate definition and exceptions, so a blanket 'every vendor needs a BAA' rule is inaccurate. We create a vendor and data-flow inventory for your counsel or privacy owner to review, and the responsible party completes the required agreement before that service handles PHI.
Those vendors publish developer documentation and FHIR capabilities, but a vendor name alone is not enough to quote an integration. We verify the customer organization, endpoint, app-registration path, authentication context, supported FHIR version and resources, read or write operations, scopes, sandbox, production approval, and rate or commercial constraints. The first phase includes only the data and actions confirmed for the target workflow.
There is no universal default. A shared schema with enforced tenant identifiers can simplify aggregate operations but demands strong policy enforcement and testing. Separate schemas can create a clearer logical boundary with more migration and operational work. Separate databases or accounts can provide stronger isolation and customer-specific control with higher provisioning and reporting cost. We select and document the model from risk, buyer requirements, scale, restore needs, and team capability.
Yes, after an architecture and data audit. We identify tenant ownership for every record, shared reference data, background jobs, files, integrations, reports, and administrative access. The migration plan adds explicit tenant boundaries, backfills and validates ownership, tests denied cross-tenant access, rehearses rollback, and moves customers in controlled cohorts. We do not promise a migration approach or zero downtime before inspecting the current system.
We start with a data-flow inventory and classify each destination. The build then uses allowlisted telemetry fields, structured redaction, test fixtures without real PHI, restricted support access, retention rules, and automated checks for representative sensitive values. When a downstream service must receive PHI, that path is treated as part of the regulated system and reviewed with the vendor and agreement inventory.
The agreed scope can include application source code, infrastructure and deployment configuration created for the project, architecture decisions, data-flow diagrams, dependency and vendor inventory, automated tests, acceptance evidence, operating and incident runbooks, and an integration register. Accounts, licenses, third-party terms, and any exclusions are named in the contract so ownership is clear before development begins.
Work with us
Bring the target buyer, one workflow, the data it uses, and any EHR or vendor commitments already made. We will identify the first production slice, the assumptions that need proof, and the range it fits.

