


"RaftLabs elevated my ideas and brought them to life when everything seemed impossible."

Grady Lakshmono
CoFounder, Gula (acquired by Runchise)
Telehealth App Development Services
We build telehealth platforms for practices that have outgrown off-the-shelf tools. 1-on-1 and group video sessions, HIPAA-compliant storage, booking and reminders, EHR integration, scoped and priced before any code is written.
1-on-1 and group video sessions, audio, and secure text messaging
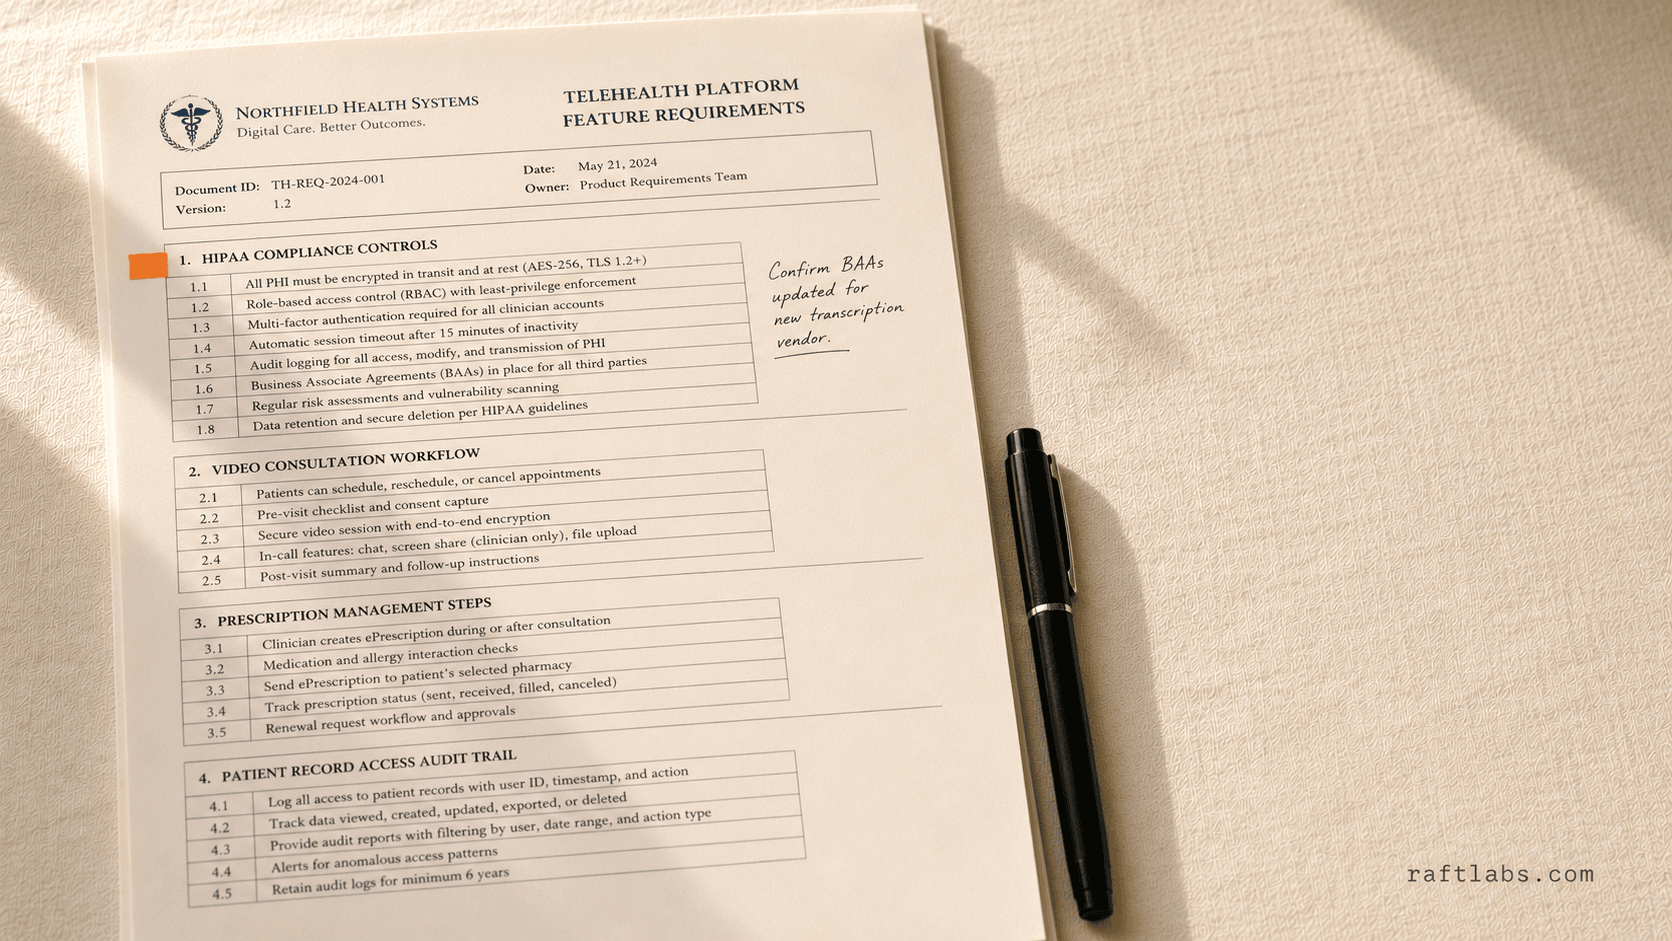
HIPAA-compliant, encrypted storage, audit trails, and role-based access
Booking, reminders, and follow-up automation built in
Works on any device, iOS, Android, and web browser
Built for general practitioners, specialists, therapists, and senior living care
Bring the problem, the current workflow, or the existing code. We reply with a practical next step within one business day.
Trusted by
























The brief
Good software decisions begin with the constraint, not a list of features or a preferred technology.
Patients dropping off because video calls freeze or appointments are hard to book?
Clinical staff spending hours on scheduling, reminders, and follow-ups that software should handle?
Per-user licensing fees that grow faster than your patient list?
Previous platform that breaks every time you add a new provider?
Plain answer
RaftLabs builds custom telehealth apps for practices across the US, UK, Europe, Canada, GCC, South Africa, and Southeast Asia. Services include video consultations, HIPAA-compliant storage, EHR integration, and booking automation. A focused web release starts around $40K and usually takes 12 to 16 weeks. Scope and a fixed price are locked before any code is written.
What to remember
A patient with a mobility limit books a follow-up and waits for the call to connect. It drops once, then twice. She gives up, and she doesn't rebook. Down the hall, the front desk spends the afternoon on reminder calls the software should be placing on its own. And every new provider the practice brings on nudges the per-seat licence bill up again.
The care was never the problem. The platform was.
According to Deloitte's 2024 Global Health Care Consumer Survey, 44% of patients had a virtual visit in the previous 12 months, and 94% of those patients said they would do it again. Practices that have not built a reliable telehealth channel are losing return visits to competitors who have.
RaftLabs builds telehealth platforms for practices across the US, UK, Europe, Canada, the GCC, South Africa, and Southeast Asia. One recent build onboarded 50+ clinics in 12 weeks and cut in-person visits by 60%. The team that scopes your platform in Week 1 is the team that ships it. RaftLabs has shipped production software since 2015 for clients across the US, UK, Europe, Canada, and the UAE.
Everything on the left should already be true for your practice. Even one thing on the right, and a configured off-the-shelf tool is the smarter first step.
An established practice, general practice, specialist clinic, therapy group, or senior living provider, already running repeat virtual or in-person visits.
An existing EHR such as Epic, Cerner, Athenahealth, or Greenway Health that the platform needs to read from and write back to.
Budget for a fixed-price build, and a decision-maker who can define the clinical workflow.
A solo provider who just needs the occasional one-to-one video call an off-the-shelf tool already covers.
A standard scheduling-and-video need a configured white-label tool already handles well.
No budget yet, or clinical requirements still forming.
It is whether software is the right answer at all. We use four possible recommendations before discussing a development scope.
Choose a maintained product when it handles the core workflow and the remaining gaps can be solved with configuration, a connector, or a small process change. Paying for software you do not have to maintain is often the better trade.
Keep the existing product when users still get value from it and the code can be understood safely. Start with evidence: where the code lives, how the data is organized, what is tested, which outside services it depends on, who can access what, and how updates go live.
Own the system when the care visit shapes margin, customer experience, speed, or a product customers pay for. Start with one complete path and the system connections that path cannot work without.
Do not turn a changing policy into permanent software. Stabilise the rules, name the workflow owner, and measure the cost of the current process before paying for a product.
Not sure which path is yours? Bring it to a 30-minute call. Leave with the answer in writing.
What we build
Encrypted storage, audit trails, and role-based access control are part of the base architecture, not an add-on. PHI is encrypted at rest with AES-256 and in transit with TLS 1.3, access control is enforced at the API layer so a front-end bypass cannot expose records, and every record access is written to an immutable audit log. BAAs are signed before development begins.
We have shipped telehealth platforms, remote patient monitoring apps, and patient portals for practices in the US, UK, and Ireland, so HIPAA safeguards, NHS DSP Toolkit requirements, and GDPR health data obligations are familiar ground. We know how a GP's follow-up booking differs from a specialist's referral queue, and those differences shape data models, not just UI. You are not paying for our learning curve.
Scope and price are locked before a line of code is written. You receive a fixed price at the end of Week 1 discovery, after we map your patient population, providers, systems, and compliance requirements. Payment is structured against working-software milestones: design sign-off, MVP feature complete, QA sign-off, production launch. The fixed price you receive in Week 1 is the number you pay.
The period after launch is when real patient and provider load exposes issues staging cannot: concurrent booking edge cases, video degradation on poor networks, EHR sync failures. We monitor production error rates and latency with CloudWatch or Datadog so problems are caught by our alerts, not your patients.
HL7 FHIR R4 is our integration standard for EHR connectivity, with read/write integrations built against Epic, Cerner, Athenahealth, and Greenway Health, so patient demographics, appointments, and clinical notes sync bidirectionally where the EHR allows. Twilio Video or Daily.co handles sessions, Stripe handles payments and co-pay collection, and Twilio SMS and SendGrid handle reminders. Your existing tools stay in place.
Working software is demonstrated every two weeks, not slides or status meetings. Every sprint ends with a live demo in a staging environment that mirrors production, where you and your clinical team test the flows as a real provider and patient would. Problems surface when they are cheap to fix, and you see what you are paying for at every demo.
Every choice, from scaling to accessibility, is made around real clinical use.
Telehealth platforms built on AWS with auto-scaling handle busy periods without manual provisioning. The application layer scales horizontally against session count, PostgreSQL with read replicas and connection pooling prevents exhaustion under load, and Twilio Video keeps sessions stable with automatic relay fallback. Multi-tenancy is designed in from the start.
Software designed around clinical workflows fits clinical work better than generic SaaS patterns. We map your actual workflow in Week 1: how a GP books follow-ups, how a specialist handles referrals, how a chronic-disease nurse tracks RPM alert thresholds. That mapping drives the data model and the UX, so clinical staff recognize their workflow on screen instead of adapting to what the software expects.
Patient and provider interfaces are tested on iOS, Android, and desktop browsers in every sprint QA cycle, not at launch. Video sessions use WebRTC (Twilio Video or Daily.co) and run in-browser on all modern platforms, no plugin or download for occasional patients, while native iOS and Android apps are available where push notifications and offline care-plan access matter.
HIPAA Technical Safeguards are part of the infrastructure, not patched on later: unique authentication for every user, automatic session timeout, and MFA for admin roles. TLS 1.3 is enforced on all API and video traffic, immutable audit logs record every PHI access stored separately, and penetration testing against OWASP Top 10 and the HIPAA Security Rule runs before launch.
Manual scheduling, reminder calls, and follow-up coordination are the largest time sinks in telehealth operations, and the most automatable. Automated reminders via Twilio SMS and SendGrid email at 48, 24, and 2 hours before appointments cut no-shows, and cancellation and rescheduling policies enforce themselves, returning slots to availability without staff involvement.
The patients who benefit most from telehealth, those with mobility limits, chronic conditions, or low comfort with complex interfaces, are the most likely to abandon a poorly designed platform. We design for them: large touch targets, three taps from reminder link to live video session, and readable default typography, with multi-language and RTL support and WCAG 2.1 AA accessibility guidance applied to all patient-facing web interfaces as standard.
Store-and-forward or live video dermatology review built around a clinician-owned workflow: patient intake and consent, clinician-approved image capture with retake requests, a review queue that keeps history and image versions together, and escalation with follow-up. The software never diagnoses; the clinician owns clinical adequacy, urgency, and treatment.
Walk us through your clinical workflow and what your current platform can't handle. The call is the intro; a costed scope follows within about two business days.
How it works
Every telehealth project follows the same phases. Compliance is designed in from Week 1, not bolted on before launch.
Discovery is a structured working session with your clinical and operational leads, not a questionnaire. We map your patient population and care pathways: what conditions are being managed, what appointment types exist (initial consultation, follow-up, group session, crisis check-in), what documentation is required post-session (session note, care plan update, prescription, referral). We map your existing systems: EHR vendor and version, billing system, practice management software, and any current video or messaging tools your providers are already using. We identify the compliance context: US HIPAA, UK NHS DSP Toolkit, GDPR, or state-specific telehealth regulations for interstate practice. By the end of Week 1, we have a scope document, a technical architecture outline, and a fixed price. You approve it before development begins. Nothing is built on an estimate.
Every patient and provider flow is wireframed and prototyped before any code is written. Patient flows cover registration, booking, pre-appointment forms, session join, and follow-up scheduling. Provider flows cover the daily schedule, patient queue, session notes, prescriptions, and referrals. Each wireframe is reviewed with the clinician who will use it daily, not just the project sponsor. Design sign-off is a formal milestone: you approve the product before it is built, so there are no mid-sprint surprises.
Two-week sprints, each with a clear goal and a working demo at the end. Sprint order puts the highest-risk integrations first: video infrastructure and authentication in Sprint 1, booking in Sprint 2, EHR FHIR integration in Sprint 3, then session notes, messaging, billing, and advanced features per your scope. Each demo runs in staging with anonymized test patient data. Engineers, QA, and your clinical reviewer attend every demo so feedback is immediate.
QA runs in parallel with development, not as a phase after the build. Automated end-to-end tests with Playwright cover critical patient and provider journeys. Manual testing targets clinical edge cases: a patient joining 20 minutes early, a provider switching devices mid-session, an EHR sync failure mid-appointment. A HIPAA compliance review covers PHI access paths, encryption, and audit log completeness before anything ships. Penetration testing against OWASP Top 10 is completed before go-live.
Production deployment follows a defined runbook: infrastructure via Terraform, database migration with tested rollback scripts, and load testing with k6 at twice your expected peak before the first patient is onboarded. App Store and Google Play submission is handled if native apps are in scope, including healthcare category review preparation. For large practices we recommend a phased rollout: a pilot cohort first, 48 hours of monitoring, then full rollout.
After launch, the platform improves on data from real clinical use, not assumptions. We monitor error rates, session completion, and booking abandonment, with structured provider check-ins at weeks 2, 4, and 8. The monitoring setup (CloudWatch or Datadog dashboards) is handed to your team with runbooks for the most common operational issues. Ongoing feature development is available afterwards as a fixed monthly retainer.
What clients say
Three-year average engagement. Founders and operators describing the work in their own words. No marketing varnish.
I was pleased with RaftLabs team's quality, consistency and execution.
Dr.J. Ayo Akinyele
President, Co-Founder, Yeletech Security Inc & Bolt
"RaftLabs elevated my ideas and brought them to life when everything seemed impossible."
Grady Lakshmono
CoFounder, Gula (acquired by Runchise)
"What distinguished RaftLabs from other providers was their fantastic ability to build real-time engagement-based products."
Georgina D.
CEO & Co-Founder, People Supported Technologies
Proof
Work with us
Bring the rough workflow, half-built product, or messy brief. We will map the smallest useful first move, then send scope, timeline, and price in plain English.
Straight answers to what buyers ask before they scope. Still stuck? .
Telehealth apps reduce no-show rates, cut travel time for patients with mobility or location constraints, and lower per-visit operational costs for providers. For chronic disease management, remote monitoring through a telehealth platform can catch deterioration earlier than quarterly in-person appointments.
We build custom telehealth platforms, not white-label tools. That includes 1-on-1 and group video consultation systems, asynchronous messaging platforms for specialists, store-and-forward dermatology workflows, remote patient monitoring apps connected to CGM and BPM devices, and patient portals that connect to your existing EHR and billing system. We've shipped telehealth apps for general practitioners, therapists, senior living providers, and specialist clinics.
It depends on feature scope and EHR integration requirements. We map your exact requirements in the first week and lock scope and a fixed price before any code is written; the timeline comes out of that scoping, not before. A focused web release usually takes 12 to 16 weeks, as the cost answer below sets out. The calendar holds more than building: the HIPAA safeguards are designed and reviewed, the EHR connection is tested before launch, the video vendor BAA is signed, and a security review and penetration testing run before launch. EHR vendor review queues move at the vendor's pace, and controlled-substance prescribing rules, where they are in scope, stretch the calendar in the same way.
Yes. Every telehealth platform we build is custom-scoped to your clinical workflow, patient population, and compliance requirements. We map your provider types, scheduling logic, and existing tools in Week 1. Nothing is off-the-shelf.
A focused web release starts around $40K and usually takes 12 to 16 weeks: one care journey, approved video, scheduling and intake, clinician workflow, patient access, and one integration. Native apps, EHR write-back, e-prescribing, devices, billing, several specialties, or multiple jurisdictions add scope. The largest cost variables are the number of patient and clinician journeys, integration depth, and third-party clinical services like video and prescribing, whose approvals affect time as much as engineering does. We test those assumptions in Week 1 discovery, then lock scope and a fixed price before any code is written. A complete quote names the patient and clinician journeys in scope, the video and prescribing services it uses, the depth of the EHR connection, and what is left out. Any change after that is priced and approved in writing before the work is done.
Compliance is the sum of safeguards maintained over time: encrypted video and storage, role-based access with multi-factor authentication, auto timeouts, audit trails, BAAs with every subprocessor including the video vendor, PHI-free notifications, and a tested breach plan. We do not certify HIPAA compliance; only your compliance team can assess that. We build the technical foundations that make it achievable. The obligation itself is your practice's: HIPAA applies to any system that holds patient information, including the booking and intake parts of this one, not only the video visit. Compliance is shared. The build carries the technical safeguards; your practice still owns its policies, staff training, and the evidence its compliance team assesses. No software purchase makes a practice compliant on its own.
Video: one-to-one with audio-only fallback, screen share, and reconnect. Defer multi-party, whiteboard, and recording. Every video vendor needs a signed BAA. E-prescribing in phases: non-controlled via a certified vendor in the MVP; controlled substances, with identity proofing, two-factor signing, and prescription monitoring checks, in a later phase. EHR vendor review queues and controlled-substance rules are the two timeline stretchers, so scope them in week one.
Active insurance does not automatically mean telehealth coverage. Verify telehealth benefit eligibility, covered service types, provider eligibility, state rules, and payer billing rules, down to CPT code, specialty, place of service, and modifiers. Run eligibility checks 48 hours before and again the morning of the visit.
Run the MVP split: waiting-room device test, consent and intake, secure messaging, copay collection, non-controlled e-prescribing, EHR read-demographics and write-signed-note belong in the MVP. Defer interpreter joining, AI scribe, order sets, real-time eligibility and claims. Check the compliance story: is every third-party integration carrying a BAA?
Yes. We sign a mutual NDA before any project discussion begins. For healthcare projects, we also sign a Business Associate Agreement (BAA) as required under HIPAA before any protected health information is shared. Both documents are standard for us and are provided at the start of discovery with no negotiation delay on our side.
Patient identity, consent, structured history, image guidance and upload, appointment or asynchronous intake, clinician queues, comparison views, documentation, messaging, escalation, referral, follow-up, notifications, role access, audit, and integration. Clinicians define the required evidence and remain responsible for clinical decisions.
No. Image-only assessment can miss context and quality problems. Any decision-support feature needs clinician-defined intended use, evaluation, oversight, monitoring, and the appropriate regulatory review. The clinician or care organisation owns diagnosis, treatment, urgency, and patient communication.
With clinician-approved capture guidance, required views, device and file checks, visible quality prompts, retake requests, and an exception path. A technical quality score cannot settle clinical adequacy; the reviewing clinician decides whether the evidence is sufficient, requests more, escalates, or changes the consultation mode.
Both are established. Store-and-forward suits asynchronous review on the clinician's own schedule; live video suits visits needing real-time interaction. Some states require a video visit to establish the patient relationship, so confirm the rules for your markets. A hybrid is common: in-person for complex lesions and procedures, virtual for routine follow-ups.
Common models are fee-for-service billing, capitated service contracts, per-case contracts, and direct-to-consumer. Reimbursement rules vary by payer and state, so confirm the codes and eligibility rules for your markets with your billing advisers before launch.
You do, from day one. The code, the cloud and video accounts, and the documentation are in your practice's name and under your control from the start, not handed over at the end. Patient data stays yours throughout. Notes are kept current as the work happens, so another team could pick the platform up at any point.
You already hold everything: the code, the accounts in your name, the patient data, and current notes, so there is nothing to extract and no unlock step. We do not offer source-code escrow, because there is nothing held back for escrow to release.
Penetration testing is taken care of before launch. No production patient data is used in development, ever: building and testing run on anonymized test patient data. Tested backups run throughout, and offboarding steps are followed when someone leaves the team, so their access ends with their work. The third parties this platform sends patient data to by design, such as the video provider, the cloud host, and the EHR connections in scope, are named in the scope document before signing, including which of them process patient data and the BAA each one needs. We claim practices we can show you, not certifications.
After launch you can continue with another fixed phase, move to an ongoing engagement, or have your own team run the platform from the monitoring setup and runbooks handed over at launch. Whoever runs it, a live telehealth platform carries standing costs: video platform fees, hosting, EHR integration and API access fees, messaging fees for reminders, and e-prescribing vendor fees where prescribing is in scope. Scoping names those costs before you sign, so they are part of the decision, not a surprise after launch.
We work on five principles. Switch to Async: progress and questions are written down, so you can check them between clinics instead of waiting for a call. Be Prepared: every demo and decision meeting comes with what you need to decide, shared in advance. Write: decisions, scope changes, and open questions live in writing, not in call memory. Ask and tell: we ask when something is unclear and tell you early when something changes. Own: the person who takes a point owns it until it is closed. Working software is demonstrated every two weeks, so you can see progress rather than read about it.
No. The team that scopes your platform is the team that builds it: the people on your calls are the people on your project. Our headquarters are in India & Ireland. The video, messaging, and EHR services the platform connects to are systems it uses, not a handoff of your project.
What it costs
The first phase ships one visit path: video, booking, reminders, HIPAA storage, and one EHR connection.
Starting investment
Starts at $10K
A bounded telehealth release covering one visit type with compliant storage and one integration. After a 30-minute call, you get a written build, buy, repair, or wait recommendation plus first-phase direction. Free, whether or not you build with us.
