"RaftLabs has been an exceptional partner. From the start, they became more than just a service provider, they embraced our vision with their expertise and dedication. We're proud of the result."

Jennyfer Ngueno
CoFounder & CEO, Sekou
Healthcare Software Development Services
We build healthcare software for practices, clinics, and health systems: patient portals, telehealth, RPM, clinical decision support, and EHR integrations. HIPAA safeguards built in from week one. Fixed price, with a validated v1 first and the full platform grown from there.
HIPAA safeguards built in from the start, not bolted on before launch
Connects to your existing EHR, billing, scheduling, and wearable device feeds
Patient portals, telehealth, RPM, and clinical decision support built to your exact workflow
25+ clinics adopted our RPM platform in 60 days
Launch a validated v1 first, then grow it into the full platform
Bring the problem, the current workflow, or the existing code. We reply with a practical next step within one business day.
Trusted by
























The brief
Good software decisions begin with the constraint, not a list of features or a preferred technology.
Clinical staff spending 2+ hours a day on documentation instead of patient care?
EHR that doesn't talk to your billing system, scheduling tool, or patient portal?
Per-seat licensing fees that scale with your team, not your revenue?
Previous software that nobody fully understands anymore?
Plain answer
RaftLabs builds healthcare software with HIPAA safeguards for US practices and health systems: patient portals, telehealth, remote patient monitoring, and EHR integrations over HL7 FHIR R4. Our RPM platform reached 25+ clinics in 60 days. Fixed price, with a validated v1 first and full platforms growing from there.
What to remember
A nurse finishes a visit and spends the next twenty minutes re-keying the same numbers into systems that do not talk to each other. The EHR does not pass to billing. Billing does not pass to the patient portal. So someone types it all again, and the clinical staff you hired to care for patients spend two hours a day on documentation instead.
None of it is bad software. It is average software, sold to every practice the same way, and your workflow is not average. The per-seat license grows with your team, not your revenue, and the one person who fully understood the setup is no longer around.
Custom healthcare software removes the re-keying. The systems connect, the record is one record, and the workflow fits the way your clinic actually runs.
Generic clinical tools are built for the average practice. When your workflows, compliance requirements, or patient data do not fit the template, staff spend the day working around the software instead of using it.
RaftLabs has shipped healthcare products with HIPAA safeguards since 2015. A nurse-assisted telehealth platform onboarded 50+ clinics in its first 12 weeks. A remote patient monitoring platform reached 25+ clinics within 60 days, and we later added an AI layer to it. RaftLabs has shipped production software since 2015 for clients across the US, UK, Europe, Canada, and the UAE. One team scopes the clinical workflow, builds the system, integrates it with your existing EHR, and hands it over, with HIPAA safeguards designed in from week one, not retrofitted before launch. Connecting to an existing record system? See EHR and EMR integration. Building for patients directly? See patient portal development.
Healthcare software failures do not fail quietly. According to the IBM Cost of a Data Breach Report 2025, the average healthcare data breach now costs $7.42 million, the highest of any industry for the 14th consecutive year. And a bad implementation does not need a breach to do damage: KLAS Research's 2024 survey of EHR go-lives found only 38% of implementations fully met the expectations set before the project started.
The two named incidents below are not hypotheticals. They are what happens when clinical software ships without the safeguards or the scoping discipline built in from day one.
MD Anderson Cancer Center's 2016 Epic EHR rollout is the textbook case. Adjusted income fell 76.9% over the following ten months, and the center posted a $266 million operating loss for the year. Roughly 900 staff were laid off in the aftermath, largely attributed to the disruption of the transition. The system itself worked. The rollout did not account for how the clinical and billing workflows actually ran.
The second incident is more recent, and it answers a question most healthcare buyers ask us directly: what happens if the vendor gets breached, not us? In February 2025, Oracle Health (formerly Cerner) disclosed a breach that, per HIPAA Journal and Becker's Hospital Review, has been confirmed across 17+ health systems, with plaintiffs' counsel citing Oracle's own figures putting the number as high as 80 hospitals.
Everything on the left should already be true for your practice. Even one thing on the right, and a configured off-the-shelf tool is the smarter spend right now.
A clinical workflow, compliance requirement, or patient-data structure that off-the-shelf healthcare tools can't fit.
An existing EHR, billing, or scheduling system the new software has to connect to, not replace.
A decision-maker who can sign off on scope, and budget for a fixed-price build.
A standard need a configured practice-management or EHR product already covers well.
No budget yet and requirements still forming.
Shopping for the cheapest hourly team, not a fixed-scope partner.
It is whether custom healthcare software is the right answer at all. We use four possible recommendations before discussing a development scope.
Choose a maintained product when it handles the core workflow and the remaining gaps can be solved with configuration, a connector, or a small process change. Paying for healthcare software you do not have to maintain is often the better trade.
Keep the existing product when users still get value from it and the code can be understood safely. Start with evidence: where the code lives, how the data is organized, what is tested, which outside services it depends on, who can access what, and how updates go live.
Own healthcare software when the workflow shapes margin, customer experience, speed, or a product customers pay for. Start with one complete path and the system connections that path cannot work without.
Do not turn a changing policy into permanent software. Stabilise the rules, name the workflow owner, and measure the cost of the current process before paying for a product.
Not sure which path is yours? Bring it to a 30-minute call. Leave with the answer in writing.
Healthcare products must account for clinical workflows, compliance risks, data interoperability, and the business decision to buy, build, or wait. Explore the challenges healthcare teams face and how to evaluate the right approach.
What we build
HIPAA-compliant iOS and Android apps for patients and clinicians: telehealth, medication management, RPM companion apps, and health tracking, built in React Native or native Swift and Kotlin where performance demands it.
Multi-tenant healthcare SaaS with subscription billing, tenant isolation for PHI, and self-service onboarding, architected so cost-per-clinic and enterprise readiness are decided in sprint one.
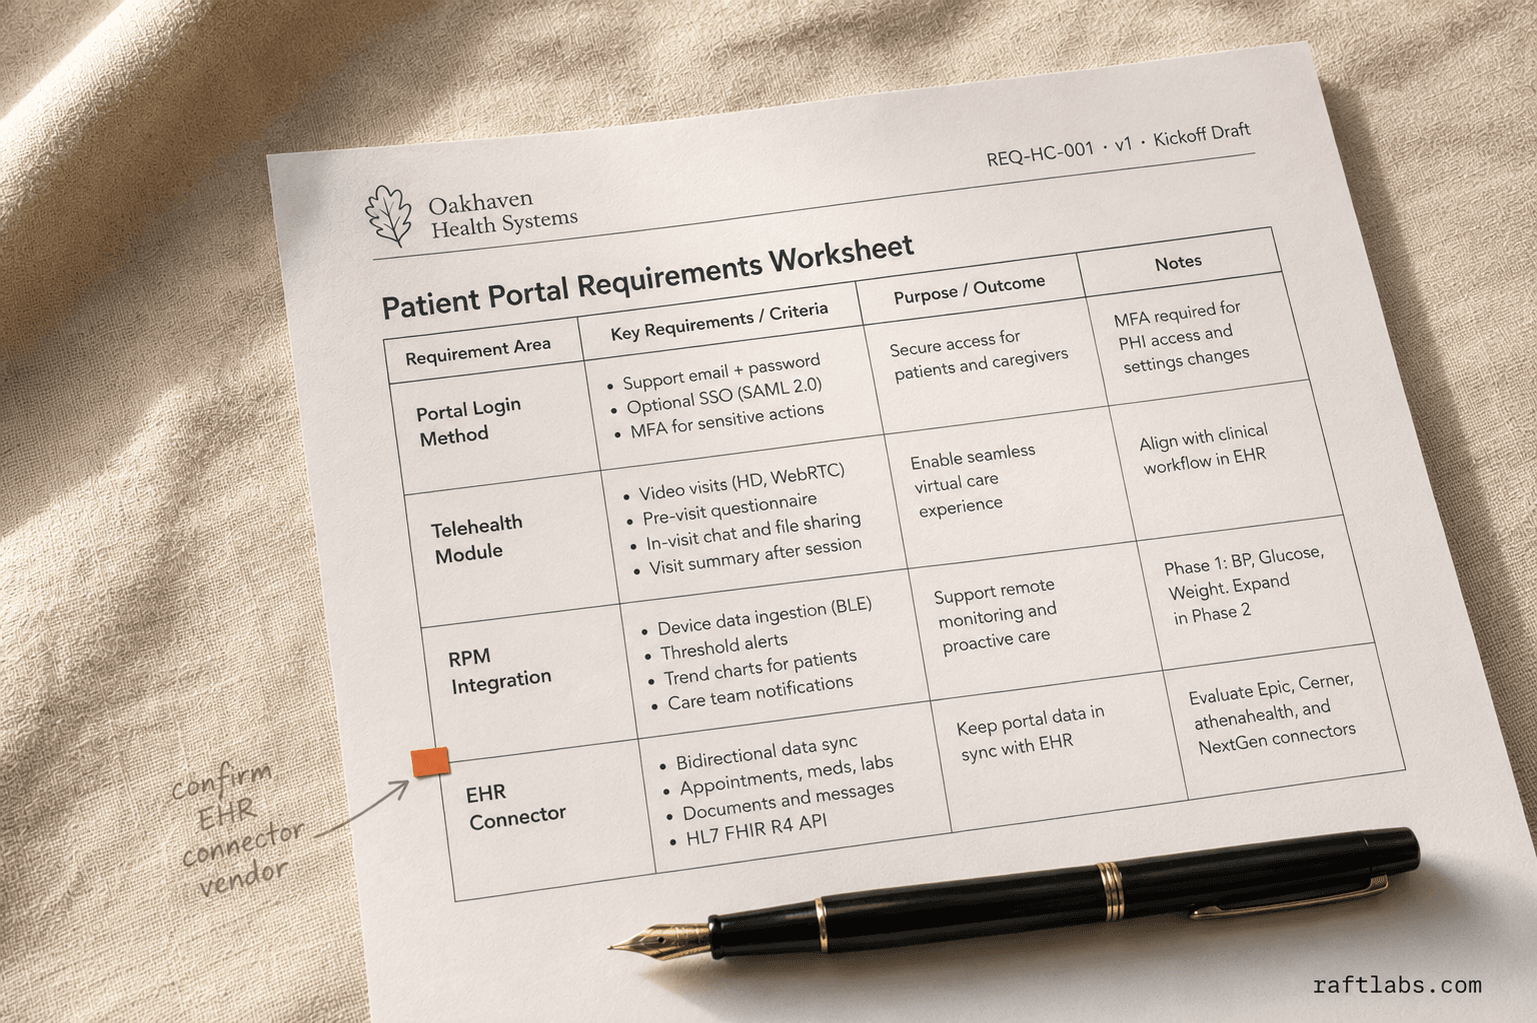
Bidirectional EHR connectivity via HL7 FHIR R4 and HL7 v2: Epic App Orchard, Cerner FHIR Millennium, Athenahealth, and Meditech, for demographics, appointments, clinical notes, results, and medication lists.
Secure patient portals for scheduling, records access, secure messaging, and results, wired to your EHR so patients and staff work from one record, not two parallel systems.
RPM platforms that ingest data from CGM, blood pressure monitors, pulse oximeters, and connected scales, with automated threshold alerting and a provider dashboard for chronic care programs.
HIPAA-eligible video sessions, secure messaging, and asynchronous consultation workflows on Twilio Video or Daily.co WebRTC, with EHR integration for scheduling and clinical documentation.
Automation for prior authorization, patient intake, scheduling, and billing, cutting the manual documentation and data re-entry that pulls clinical staff away from patient care.
We have shipped a nurse-assisted telehealth platform that onboarded 50+ clinics in its first 12 weeks and a remote patient monitoring platform 25+ clinics adopted within 60 days. That domain knowledge shapes every architecture decision from week one, so you do not pay for us to learn what the HIPAA Security Rule's technical safeguards mean or what an Epic or Cerner integration needs to pass vendor review.
Milestone-based pricing with the fixed total agreed and documented before development starts, not a time-and-materials contract where the number depends on hours logged. The project breaks into milestones, each with a defined deliverable and payment, and you see working software at every bi-weekly sprint review. If scope changes, the change is costed and approved explicitly before any additional work begins.
No handoffs between a business analyst who scoped it, a design team who doesn't know the clinical workflow, and an offshore build team who has never spoken to the client. The same engineers who run discovery and review the wireframes with your clinical team are the ones who write the code, so accountability never gets diluted across a handoff chain.
Every dependency is chosen because it is fit for healthcare, not because it is the most popular option. Web interfaces and patient portals, cross-platform mobile, and PHI storage with row-level security, plus a health-specific layer for EHR connectivity, HIPAA-eligible video sessions, and device integrations for CGM, blood pressure, and pulse oximetry.
We connect the new system to your existing EHR, billing software, scheduling tool, and third-party device feeds. No rip-and-replace: your staff keeps the systems they know, and the new platform adds capabilities without creating two parallel records for every patient. Every integration is tested against a sandbox instance of your EHR before any production cutover.
8 weeks of post-launch support is included in every fixed-price engagement: bug fixes for issues discovered under real patient load, monitoring alert investigation, performance tuning, and on-call availability during the first 30 days, when clinical workflow edge cases most commonly surface. Support does not expire at a calendar deadline: if the system has stability issues, we stay until it runs reliably.
Healthcare software operates under multiple overlapping regulatory frameworks. We scope compliance requirements in week one and build them into the architecture before any code is written.
According to Gartner's 2025 Enterprise IT Spending Forecast, global healthcare and life sciences IT spending is projected to reach $311 billion in 2025, growing at 7.3% year-over-year. That investment is accelerating demand for compliant, interoperable platforms built to clinical-grade standards rather than adapted from generic software toolkits.
We build to the HIPAA Security Rule's administrative, physical, and technical safeguards: PHI encrypted at rest (AES-256) and in transit (TLS 1.3), multi-factor authentication, role-based access control, session timeout enforcement, and immutable audit logs recording every PHI access event. The HITECH Act's breach-notification duties shape the logging and monitoring design, so an incident is detectable and reportable inside the 60-day window. Business Associate Agreements cover AWS, Twilio, Stripe, and every provider that touches patient data.
When you sell into hospitals and payers, their vendor-security review asks for SOC 2. We build with the Trust Services Criteria in mind from sprint one: change management, access logging, encryption, and third-party vendor management documented as the system is built, not reconstructed the week before the audit. We are not your auditor, but we build so a SOC 2 Type II report is a reporting exercise rather than a re-architecture.
EHR integration via HL7 FHIR R4 APIs for patient demographics, appointments, clinical notes, results, and medication lists. Epic App Orchard, Cerner FHIR Millennium, and Athenahealth API connectivity. For systems without a FHIR-capable API, HL7 v2 message-based integration handles bidirectional data exchange.
For platforms required to support ONC Cures Act Final Rule compliance, we implement SMART on FHIR authorization, FHIR R4 patient access APIs, and the audit logging required for ONC compliance reviews. Information-blocking prohibitions are accounted for in the data access design.
For platforms serving European patients, we scope GDPR requirements: data processing agreements, consent management, right-to-erasure workflows for patient records, and data residency controls keeping PHI within EU infrastructure. UK GDPR requirements for post-Brexit deployments are handled separately where applicable.
For software as a medical device (SaMD), we scope regulatory classification, document software development lifecycle requirements for the target classification, and prepare quality management system documentation for regulatory submission.
DICOM-compliant image handling for platforms that store, transmit, or display medical images. PACS integration, DICOM viewer embedding via open-source renderers (OHIF, Cornerstone.js), and compliant storage on HIPAA-eligible infrastructure with appropriate encryption and access controls.
AI in healthcare software is not one thing. There is the back-office layer, prior-authorization drafting, documentation summarization, intake triage, where a wrong answer means a human catches it. And there is the clinical-decision layer, where a wrong answer reaches a patient. We build aggressively in the first and conservatively in the second.
The demand is real. The American Medical Association's Augmented Intelligence survey found physician AI adoption jumped from 38% in 2023 to 66% in 2024, with documentation and administrative relief the top use cases. That is where the honest wins are: taking the two hours a day of re-keying off clinical staff, not replacing clinical judgment.
Where we hold the line: any AI output that informs a clinical decision ships with a clinician in the loop, a full audit trail, and drift monitoring. The moment a model drives diagnosis or treatment without a clinician's sign-off, it crosses into software-as-a-medical-device territory (FDA 21 CFR Part 11, IEC 62304), and that is a regulatory program, not a feature. We scope that line in week one, so you know which side of it your build sits on before you commit the budget.
In healthcare, the software has to work every time. We build systems that handle the load, stay compliant, and connect to what you already use.
Custom healthcare software designed around your specific clinical workflow, not configured from a vendor template built for a different care model: telehealth platforms, remote patient monitoring, HIPAA-compliant EHR/EMR tools, chronic disease management, medication adherence, and clinical decision support. Each build starts with a one-week discovery mapping the clinical workflow with your care team.
Custom clinical and operational analytics dashboards that surface the KPIs your leadership and clinical teams need, built from your actual data: operational views for practice managers, clinical quality views for medical directors, and population health views for value-based care contracts. All dashboards pull from your existing EHR, billing, and RPM data without manual export, refreshed daily or in near-real-time.
Replace legacy EHR systems, outdated patient portals, and desktop-only clinical software with modern, secure, maintainable platforms, without the clinical disruption of a hard cutover. We use a strangler fig pattern: the new system runs alongside the legacy one, workflows migrate one at a time, and data migration is validated with reconciliation checks before any cutover.
Connect your new or existing platform to the clinical systems already in use: EHR integration via FHIR R4, e-prescribing, plus scheduling, billing, and telehealth video infrastructure. Each integration is assessed for the correct API approach and tested against the vendor's sandbox before production, so data flows without manual re-entry.
Reduce page load times, cut database query latency, and automate the manual steps that slow clinical and administrative staff. We audit first, profiling the application against production traffic to find the specific queries and rendering paths causing slowdowns, then produce a fix list ranked by time saved per day for clinical staff. Results are verified with load testing under simulated clinical workload.
Intelligent healthcare software using AI where it delivers measurable improvement, not AI applied broadly because it is a trend. Examples: risk stratification models trained on your EHR data, AI-assisted symptom triage before telehealth visits, clinical decision support using RAG over your clinical knowledge base, and automated prior authorization assistance. Every model ships with an audit trail, human review for any output used in a clinical decision, and drift monitoring.
We are not tied to one framework. We pick the stack that fits your compliance, integration, and handover needs, then document every choice so any competent engineering team can maintain it. Every dependency is chosen because it is fit for healthcare, not because it is the most popular option in a non-clinical context.
| Layer | Technologies we use | Where it fits |
|---|---|---|
| Frontend | React, Next.js, TypeScript, React Native | Patient portals, clinician dashboards, and cross-platform mobile apps |
| Backend | Node.js, Python (FastAPI, Django), .NET | Clinical data processing, APIs, and business logic |
| Databases | PostgreSQL (row-level security), MongoDB | PHI storage with least-privilege access and flexible clinical schemas |
| Interoperability | HL7 FHIR R4, HL7 v2, EHR and EMR APIs | Epic, Cerner, Athenahealth, and Meditech data exchange |
| Cloud and compliance | AWS, Azure, HIPAA-eligible services | Encrypted, audited infrastructure covered by Business Associate Agreements |
The rule holds at every layer: PHI encrypted at rest and in transit, no proprietary frameworks that lock you in, and no stack we cannot hand to your team on day one. The interoperability layer does the heaviest lifting, and we scope it early through our EHR and EMR integration work so clinical data flows without manual re-entry.
Walk us through your clinical workflow and what your current systems can't handle. We'll scope the build and give you a fixed cost.
How it works
Every project follows the same four phases. Scope is locked and price is fixed before development starts.
We map your clinical workflows with the care team who will use the software daily. You leave week 1 with a written scope document, integration assessment, and a fixed-price quote. No development starts without your sign-off.
HIPAA controls, EHR integration approach, and PHI data flows are designed before any code is written. Wireframes reviewed and approved by your clinical leads. The compliance architecture is documented and locked before the build starts.
Working software at a staging URL by the end of sprint one. Bi-weekly demos with the clinical team who will use it. QA and HIPAA compliance checks run in parallel with every sprint, not as a phase at the end.
Production deployment with monitoring activated on launch day. 8 weeks of post-launch support included in every project. Bug fixes, performance tuning, and on-call availability during the critical first 30 days.
Overlaps are intentional — phases start before the previous one ends.
Proof
We've built HIPAA-compliant healthcare software for US practices and health systems. Here's what makes the difference.
A first shippable slice, one core module or workflow, goes live first. Week 1 produces a scoped, validated architecture: clinical workflow mapping, integration assessment, and wireframes reviewed with your care team. Bi-weekly sprints add scope from there, with working software at each review, UAT, and a HIPAA compliance review before deployment. Full platforms with AI and deep EHR integration grow from there.
HIPAA compliance is designed into the architecture from the first technical decision, not added as a checklist item at the end of the build. Every system ships with PHI encrypted at rest and in transit, multi-factor authentication, role-based access control with least privilege, immutable audit logs of every PHI access event, and Business Associate Agreements with every infrastructure provider that handles PHI. A compliance review before production deployment verifies all controls are implemented as designed.
We map your clinical workflows in Week 1 through structured sessions with the people who will use the software daily: nurses, physicians, front desk, and billing coordinators. The workflow they describe is always different from what the practice manager assumes, and that map drives the technical design before the database schema is finalized, not retrofitted after. Week 1 ends with a signed-off scope document and wireframes your clinical leads have approved.
Scope and cost locked before development starts in a written fixed-price proposal that defines the feature set, integration scope, compliance controls, and delivery timeline. The price you approve in Week 1 is the price you pay at the end. Changes to scope are addressed via a change request process: the change is specified, sized, costed, and approved before any additional work begins, so our incentives stay aligned with yours.
You see working software every two weeks in a live sprint demo with your clinical leads present: not slides, not screenshots, the actual running system demonstrated against real clinical scenarios by the engineer who built the feature. Problems that affect the clinical workflow surface early, when the fix is a day's work, not at the UAT review in Week 13. Issues raised at each demo are logged, prioritized, and resolved in the next sprint.
Direct access to your named project team throughout the engagement, the lead engineer, the project manager, and the QA lead, not a ticketing system or an account manager relaying messages. Weekly sync calls follow a structured agenda, with a written summary sent within 2 hours so decisions are documented. When a risk surfaces, an unavailable EHR sandbox or a slow compliance review, you hear about it the same day we know.
We provide fixed-price proposals after a scoping session. Scope, integration count, and compliance requirements are the primary cost drivers.
| Software type | What the first release covers |
|---|---|
| Patient portal | Scheduling, records access, secure messaging wired to the EHR |
| Telehealth platform | Video sessions, scheduling, clinical documentation |
| Remote patient monitoring | Device integration, threshold alerts, provider dashboard |
| EHR integration | FHIR R4 or HL7 v2 connectivity for the target system |
| Clinical data analytics and reporting dashboard | Operational and clinical dashboards from existing EHR, billing, and RPM data |
| Healthcare mobile app | iOS, Android, or cross-platform patient or clinician app |
| Complex platform | AI, RPM, EHR, and telehealth combined in one program |
Every engagement is fixed-price: scope, features, integrations, and compliance controls agreed and documented in writing before development starts. Cost changes only when scope changes, and scope changes are priced and approved explicitly before additional work begins.
Where you land depends on scope, not negotiation:
What it costs
A defined scope, integration list, and compliance controls, agreed and documented in writing before development starts.
HIPAA compliance review, QA testing, and 8 weeks of post-launch support are part of the build, not billed separately later. Cost changes only when scope changes, priced and approved before any additional work begins.
Starting investment
Starts at $10000
Scope and timeline agreed before development starts. Most teams start with one core module and expand once compliance controls are proven. After a 30-minute call, you get a written build, buy, repair, or wait recommendation plus first-phase direction. Free, whether or not you build with us.
No hourly billing
Scope and cost for each phase are locked in a written proposal before development starts. No hourly billing, no surprise invoices. A scope change is specified, sized, costed, and approved before any additional work begins.
HIPAA compliance
HIPAA compliance is designed into the architecture from the first technical decision: PHI encrypted at rest and in transit, role-based access control, immutable audit logs, and Business Associate Agreements with every infrastructure provider that handles patient data.
Proof
Three-year average engagement. Founders and operators describing the work in their own words. No marketing varnish.
"RaftLabs has been an exceptional partner. From the start, they became more than just a service provider, they embraced our vision with their expertise and dedication. We're proud of the result."
Jennyfer Ngueno
CoFounder & CEO, Sekou
Work with us
Bring the rough workflow, half-built product, or messy brief. We will map the smallest useful first move, then send scope, timeline, and price in plain English.
All healthcare software development at RaftLabs uses a secure Agile approach: two-week sprints, client reviews at every milestone, and QA testing that runs alongside development. Security is built into every stage: encrypted data storage, access controls, audit trails, and HIPAA compliance checks before any code ships to production. You see working software every two weeks, not at the end of a 14-week silence.
We launch a validated v1, a core patient portal or a single EHR integration, then grow it. Full platforms with telehealth, remote patient monitoring, deep EHR integration, or AI features build out from there. Either way, the engagement starts with discovery: stakeholder interviews, workflow mapping, and scope definition before any code is written. The first number we give you is the first shippable slice, not the whole product.
Healthcare software at RaftLabs is fixed-price, agreed before development starts. Most teams start small and expand. A focused first build, a patient portal or a single EHR integration, is priced after scoping. A full telehealth or RPM platform, or a complex system combining AI, RPM, and deep EHR integration, grows from there. The fixed price includes a HIPAA safeguards review, QA testing, and 8 weeks of post-launch support. To get a number for your specific project, start your scope.
We built a nurse-assisted telehealth platform (video consultations, connected exam-camera, otoscope, and stethoscope feeds, e-signed prescriptions) that onboarded 50+ clinics in its first 12 weeks, and a remote patient monitoring platform connected to CGM and BPM devices that 25+ clinics adopted within 60 days. We later added an AI layer to that RPM platform that cut clinical decision-making time by 20%. We understand the compliance regime: the HIPAA Security Rule, HITECH breach-notification duties, SOC 2, HL7, and FHIR. We bring that domain knowledge to every project.
For mobile: React Native for cross-platform apps, Swift for iOS, Kotlin for Android. Backend: Node.js, Python, PostgreSQL, and AWS. For compliance: encrypted storage, audit logging, and role-based access control. For integrations: HL7 FHIR APIs for EHR connectivity, Twilio for telehealth, Stripe for billing. The stack fits your specific requirements, not our defaults.
Weight your shortlist by depth, not size. A big company name does not automatically mean deep healthcare experience. Look at healthcare-specific portfolio work, not overall headcount. Push on regulatory specifics: ask which EHR platforms they have actually connected to by name. In healthcare, the people who truly understand the system at the highest levels are the people who understand how it is actually used by customers. The two-year frame: think two years ahead, not just launch day. A cheaper build that needs a full rebuild shortly after launch rarely ends up being the better deal. Call references directly. Published testimonials are curated by definition.
Certainty without evidence. Be cautious when a company promises complete compliance, a fixed budget, a short deadline, and flawless EHR integration before studying the workflow, data, architecture, and regulatory context. HIPAA compliance is shared operational work, not a badge. Developers should not pretend to replace legal, privacy, security, regulatory, or clinical experts. They should show how those people enter the delivery process. Data mapping mismatches between systems are the most frequent, highest-impact errors. They are often invisible until they affect clinical workflows or patient records.
A focused product and a complex enterprise system differ mainly in integration count and compliance surface. Timelines that seem significantly shorter than the scope suggests deserve scrutiny. The contract should cover IP, data ownership, BAA obligations, incident handling, exit terms, and knowledge transfer. Pricing and ownership belong in writing; confirm whether compliance validation and security testing are in the quote or billed later. Buy when the process is standard and an existing product fits without heavy customization. Build when the workflow is strategically important, unusually complex, poorly served by available products, or dependent on proprietary data and integrations.
Yes. We sign NDAs before any scoping conversation. Healthcare projects involve protected health information and proprietary clinical workflows. All code, architecture, and patient data remain yours. We operate under a Business Associate Agreement with every project that handles PHI, and all infrastructure providers (AWS, Twilio, Stripe) are covered by BAAs before the first byte of PHI is processed.